
Quick answer: For diagnostic lumbar puncture services, pencil-point spinal needles are the consumable line associated with subarachnoid block. The configuration in the product data is 25G / 26G / 27G x 90 / 103 / 120 mm; the sections below cover where the item is used, what it is for and how the specification should be written.
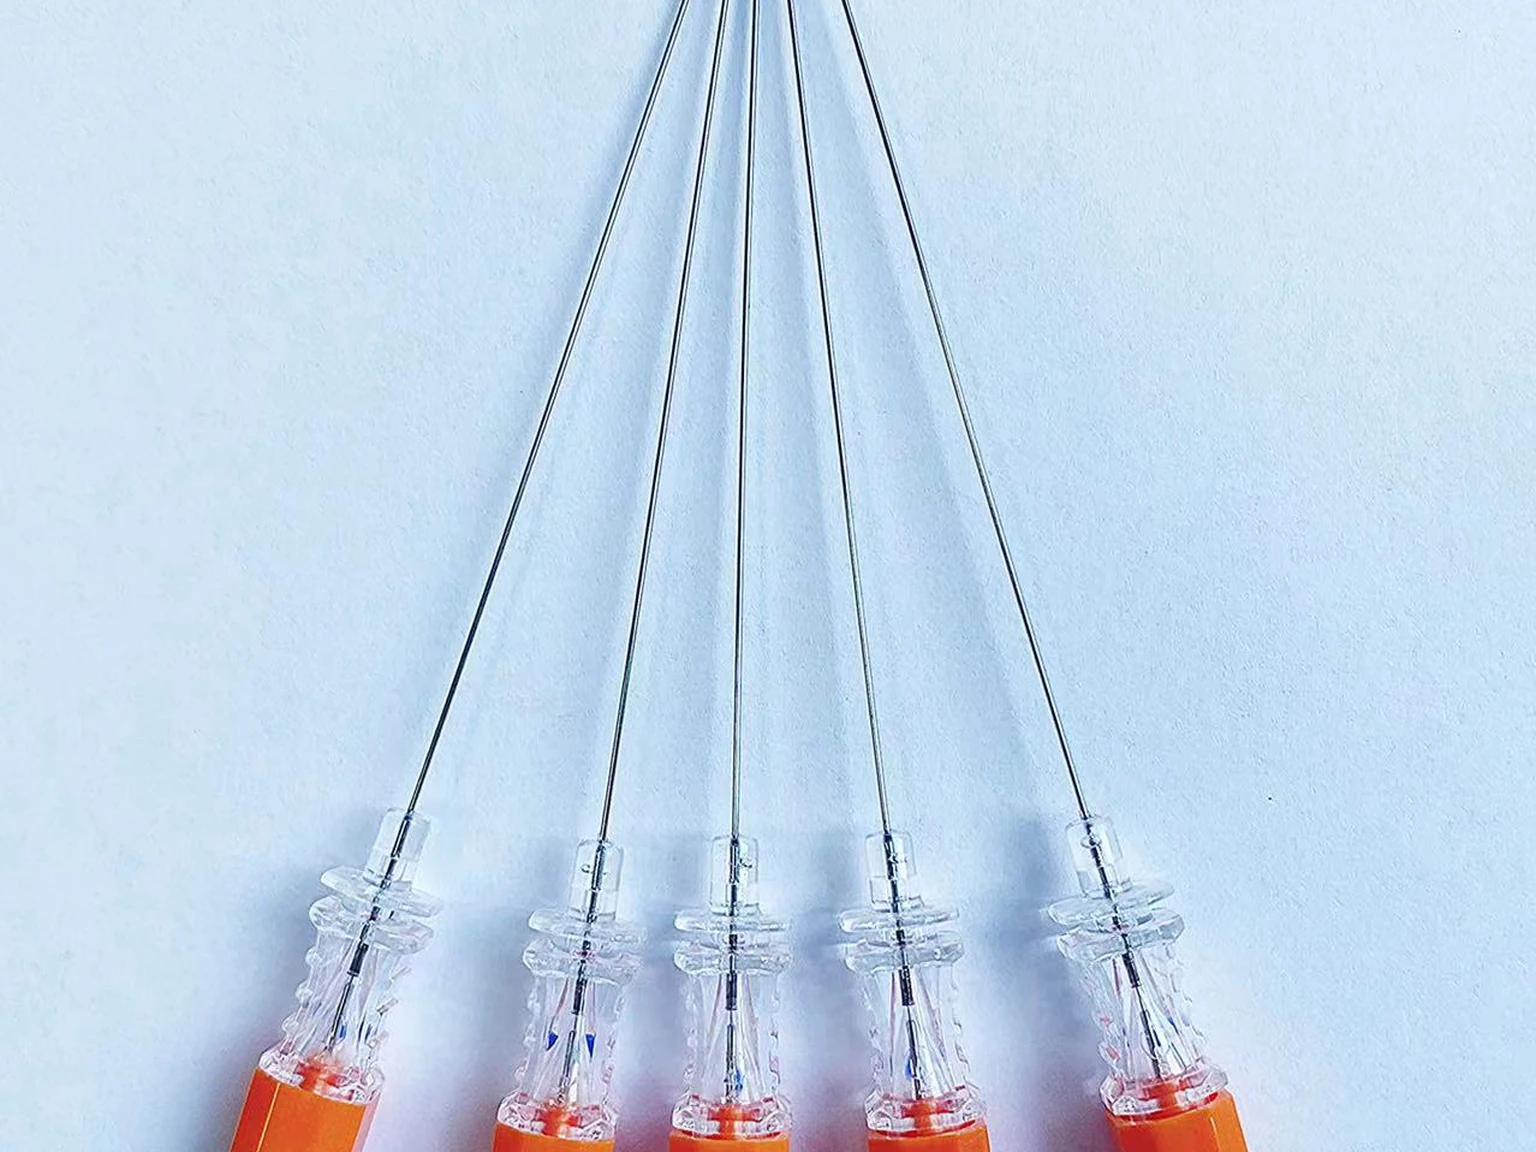
Staff Onboarding for Pencil-Point Spinal Needles in Diagnostic Lumbar Puncture Services
Handling guidance should be consistent with the labelled instructions and the department’s own protocol. Staff in emergency departments benefit from a one-page configuration card kept at the point of use. A workflow built around diagnostic request leaves little room for opening multiple separately packed items. Emergency department supply leads should record deviations and handling observations through the department’s usual reporting route.
- Handling topics for a short competency session:
- diagnostic request
- atraumatic needle selection
- aseptic collection
- post-procedure observation
- Recognition of the configuration 25G / 26G / 27G x 90 / 103 / 120 mm.
Emergency department supply leads usually require that any configuration change be confirmed in writing before the next shipment. The wording below follows the source product listing, which records settings, channels and stated uses rather than outcomes. The source listing gives the main use as subarachnoid (spinal) block with a lower risk of post-dural-puncture headache, and is suited to obstetric and younger patients, without extending the claim to other indications. The most common specification error is quoting the product family without the configuration 25G / 26G / 27G x 90 / 103 / 120 mm.
Version-locked configurations make stock reconciliation simpler because the item identity does not move. For diagnostic lumbar puncture services, the practical question is whether the configuration fits the existing routine without extra handling. When a new gauge or length is added, refresh the training note rather than relying on the old version. Long-term agreements work better when the configuration is version-locked and changes require written confirmation.
How Pencil-Point Spinal Needles Fit the Workflow in Diagnostic Lumbar Puncture Services
Teams in emergency departments usually map pencil-point spinal needles against diagnostic request before fixing a standing order. The stated use, subarachnoid (spinal) block with a lower risk of post-dural-puncture headache, and is suited to obstetric and younger patients, has to be achievable inside the existing diagnostic request routine. Application planning for pencil-point spinal needles starts with the setting: emergency departments and similar units. Pack integrity is the first visual check; configuration against the purchase order is the second.
- Workflow steps relevant to diagnostic lumbar puncture services:
- diagnostic request
- atraumatic needle selection
- aseptic collection
- post-procedure observation
For emergency departments, the relevant use case remains subarachnoid (spinal) block with a lower risk of post-dural-puncture headache, and is suited to obstetric and younger patients rather than a broader therapeutic claim. Atraumatic needle selection is the point at which pack presentation and component order matter most. Handling guidance should be consistent with the labelled instructions and the department’s own protocol. The same discipline applies across the range, from pencil-point spinal needles to Quincke spinal needles.
Reorder points should account for lead time and for any documentation checks on arrival. The wording below follows the source product listing, which records settings, channels and stated uses rather than outcomes. Where the source data notes supplied loose for OEM kit assembly or as part of a sterile pack, that statement should be quoted as written rather than expanded. A workflow built around diagnostic request leaves little room for opening multiple separately packed items.
Risk-Aware Specification of Pencil-Point Spinal Needles
Purchasing teams should ask how the chosen configuration supports the department’s existing safety protocol. Emergency department supply leads should record deviations and handling observations through the department’s usual reporting route. Specifying teams should anchor the requirement to the stated purpose, subarachnoid (spinal) block with a lower risk of post-dural-puncture headache, and is suited to obstetric and younger patients. A brief refresher after the first month usually surfaces practical issues that a tender cannot predict.
Non-conforming lots should be quarantined and recorded against the same specification used for ordering. No certification status should be assumed from a catalogue; ask for the current, valid document instead. For diagnostic lumbar puncture services, the practical question is whether the configuration fits the existing routine without extra handling. The stated use, subarachnoid (spinal) block with a lower risk of post-dural-puncture headache, and is suited to obstetric and younger patients, has to be achievable inside the existing diagnostic request routine.
The most common specification error is quoting the product family without the configuration 25G / 26G / 27G x 90 / 103 / 120 mm. Most disagreements between a buyer and a supplier turn out to be differences in configuration wording. Training and correct handling are the practical levers available to emergency departments when introducing a new consumable. Emergency department supply leads usually award on a combination of specification fit, supply continuity and document completeness.
Pencil-Point Spinal Needles: The Catalogue Definition
The GaoGuan Medical listing treats pencil-point spinal needles as a consumable line with a fixed specification of 25G / 26G / 27G x 90 / 103 / 120 mm. Pencil-point spinal needles carry the specification 25G / 26G / 27G x 90 / 103 / 120 mm, which is the baseline for acceptance checking. Pencil-point spinal needles are intended for subarachnoid block; beyond that stated use, no additional indication is claimed. Pencil-point spinal needles appear in the application list for diagnostic lumbar puncture services, specifically around emergency departments.
In practical terms the primary use is subarachnoid (spinal) block with a lower risk of post-dural-puncture headache, and is suited to obstetric and younger patients, and that purpose drives where the product is deployed. This is a descriptive comparison of catalogue configurations, not a clinical performance claim. Tender documents for pencil-point spinal needles are usually prepared by emergency department supply leads and fulfilled through Hospital tender and group purchasing. Non-conforming lots should be quarantined and recorded against the same specification used for ordering.
Repeat the same wording, 25G / 26G / 27G x 90 / 103 / 120 mm, across the purchase order, the pack label and the registration file. Review these points with emergency department supply leads before the specification is issued, not after quotations arrive. Emergency department supply leads should record deviations and handling observations through the department’s usual reporting route. Buyers will find pencil-point spinal needles under Anesthesia / Spinal Needles, where the range is described as 25G / 26G / 27G x 90 / 103 / 120 mm.
Disposable Presentation of Pencil-Point Spinal Needles
Safety discussions should stay with design intent and handling, and avoid unsupported performance claims. A sample retention and lot-traceability routine makes later investigations considerably shorter. For emergency departments, the relevant use case remains subarachnoid (spinal) block with a lower risk of post-dural-puncture headache, and is suited to obstetric and younger patients rather than a broader therapeutic claim. Atraumatic needle selection is the point at which pack presentation and component order matter most.
- Single-use and aseptic points for diagnostic lumbar puncture services:
- Confirm the disposable presentation on the label.
- Check pack integrity before opening.
- Record the lot against the department’s documentation routine.
- Dispose of the item according to the local clinical waste protocol.
The registration file should name the same configuration, 25G / 26G / 27G x 90 / 103 / 120 mm, that appears on the purchase order. Where the data is silent, the sensible approach is a qualitative requirement plus a document request. Supervisors should record which configuration each team was trained on and when. Shelf-life and rotation are managed through lot records; first-expiry-first-out is the usual rule.
Evaluation criteria should be visible to all bidders so that equivalent offers can be compared fairly. This is a descriptive comparison of catalogue configurations, not a clinical performance claim. Any complication-rate discussion belongs in the clinical literature, not in a supplier catalogue. The source data places pencil-point spinal needles in emergency departments as well as in wider distribution channels.
Common Mistakes When Sourcing Pencil-Point Spinal Needles
Skipping a written confirmation step on configuration changes undermines version control over time. Leaving the pack format undefined invites quotations that cannot be compared. When emergency department supply leads compare offers, 25G / 26G / 27G x 90 / 103 / 120 mm is the field that most often gets shortened or lost. A workable tender separates the clinical requirement, the configuration 25G / 26G / 27G x 90 / 103 / 120 mm, the pack format and the documentation set.
- Errors to avoid in diagnostic lumbar puncture services specifications:
- Omitting the configuration 25G / 26G / 27G x 90 / 103 / 120 mm.
- Treating pencil-point spinal needles and Quincke spinal needles as interchangeable.
- Leaving the pack format undefined.
- Accepting an undocumented configuration change.
A change to 25G / 26G / 27G x 90 / 103 / 120 mm or to the pack contents normally triggers a regulatory review on the buyer’s side. Non-conforming lots should be quarantined and recorded against the same specification used for ordering. Review these points with emergency department supply leads before the specification is issued, not after quotations arrive. Inventory planning for pencil-point spinal needles normally follows a size matrix, so slow-moving variants should be identified early.
Private-label programmes normally fix the configuration in writing before artwork is produced. Where the data is silent, the sensible approach is a qualitative requirement plus a document request. Approving a substitute by gauge alone misses differences in shaft, tip or matched components. Competency checks should cover aseptic opening, correct identification of 25G / 26G / 27G x 90 / 103 / 120 mm and the disposal route.
Goods-In Inspection of Pencil-Point Spinal Needles
Consistent presentation across lots matters as much as the contents of any single pack. Acceptance criteria should be written before the first delivery so that emergency department supply leads and the supplier read them the same way. Pencil-point spinal needles carry the specification 25G / 26G / 27G x 90 / 103 / 120 mm, which is the baseline for acceptance checking. Whether CE marking under MDR, FDA 510(k) clearance or another route applies depends on the destination market and must be confirmed against the supplier’s current file.
- Goods-in checks for pencil-point spinal needles:
- Label wording matches the purchase order.
- Configuration reads 25G / 26G / 27G x 90 / 103 / 120 mm.
- Pack integrity is intact and lot identification is legible.
- Documentation set matches the agreed dossier.
- Deviations are quarantined and recorded.
Reorder points should account for lead time and for any documentation checks on arrival. Record decisions in writing so that the next procurement cycle starts from a stable baseline. Skipping a written confirmation step on configuration changes undermines version control over time. Ask bidders to state any deviation from 25G / 26G / 27G x 90 / 103 / 120 mm explicitly rather than burying it in an equivalent-brand clause.
Any complication-rate discussion belongs in the clinical literature, not in a supplier catalogue. The same discipline applies across the range, from pencil-point spinal needles to Quincke spinal needles. Quality documentation is normally requested as a dossier covering the item, the configuration and the lot. For diagnostic lumbar puncture services, the relevant channel is Hospital tender and group purchasing, with emergency department supply leads drafting the requirement.
Additional Notes on Pencil-Point Spinal Needles Specification
Most disagreements between a buyer and a supplier turn out to be differences in configuration wording. Specifying teams should anchor the requirement to the stated purpose, subarachnoid (spinal) block with a lower risk of post-dural-puncture headache, and is suited to obstetric and younger patients. Configuration details such as 25G / 26G / 27G x 90 / 103 / 120 mm belong in the technical schedule, not in a separate email. Distribution is described through Hospital tender and group purchasing, which is where emergency department supply leads usually place volume orders.
At goods receipt, check label wording, lot identification, pack integrity and the stated configuration 25G / 26G / 27G x 90 / 103 / 120 mm. Keep the discussion anchored to what the specification actually says and to how emergency departments work. Standards such as ISO 13485, ISO 11135 for ethylene oxide sterilisation and ISO 10993 for biocompatibility are often referenced in tender dossiers. Reorder points should account for lead time and for any documentation checks on arrival.
Single-patient use and aseptic handling are the two safety topics most often written into diagnostic lumbar puncture services specifications. Record decisions in writing so that the next procurement cycle starts from a stable baseline. Emergency department supply leads usually award on a combination of specification fit, supply continuity and document completeness. Standardising diagnostic request is often easier than renegotiating the specification later.
Frequently asked questions
How should a size matrix for pencil-point spinal needles be planned?
For emergency departments, the relevant use case remains subarachnoid (spinal) block with a lower risk of post-dural-puncture headache, and is suited to obstetric and younger patients rather than a broader therapeutic claim. Gauge, length and configuration appear in the listing as 25G / 26G / 27G x 90 / 103 / 120 mm, so substitutions should be flagged explicitly. Where the data is silent, the sensible approach is a qualitative requirement plus a document request.
What specification should appear on a pencil-point spinal needles purchase order?
The application settings recorded for this line include emergency departments and comparable services. Distribution is described through Hospital tender and group purchasing, which is where emergency department supply leads usually place volume orders. Acceptance criteria should be written before the first delivery so that emergency department supply leads and the supplier read them the same way.
How is sterility and pack integrity checked on delivery?
No certification status should be assumed from a catalogue; ask for the current, valid document instead. Long-term agreements work better when the configuration is version-locked and changes require written confirmation. The wording below follows the source product listing, which records settings, channels and stated uses rather than outcomes.
What is the stated use of pencil-point spinal needles?
Emergency department supply leads should record deviations and handling observations through the department’s usual reporting route. In day-to-day work the sequence runs through diagnostic request, so the consumable has to fit that step without rework. A brief refresher after the first month usually surfaces practical issues that a tender cannot predict.
Continue reading
- Thread Embedding Needles Procurement Guide for TCM Rehabilitation Centres
- Thread Embedding Packs Handling Skills for TCM Rehabilitation Centres
- Quincke Spinal Needles Buying Checklist for Diagnostic Lumbar Puncture Services
- Lumbar Puncture Needles Workflow in Neurology Departments: A Practical Guide



 English
 Deutsch
 Français
 Русский
 Español
 Português
